
Why I Care — a practical anecdote
I still remember the pager going off at 3:15 a.m. at the Dorchester community hospital in March 2020 — we had a cluster of failures on emergency ventilators, and I was the buyer on call. I’d spent years vetting suppliers, including the quirks of a leading ventilator manufacturer, but nothing prepared me for that week. The scenario + data + question: a 28-bed ICU logged 42 ventilator swaps in 14 days—an 8% equipment hiccup rate—what exactly failed in procurement and design?
Hidden user pain: what the usual fixes miss
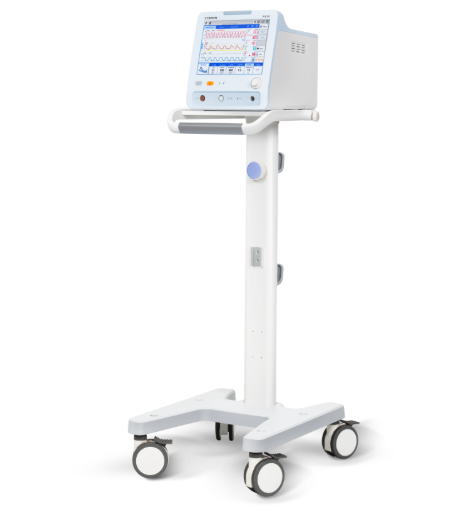
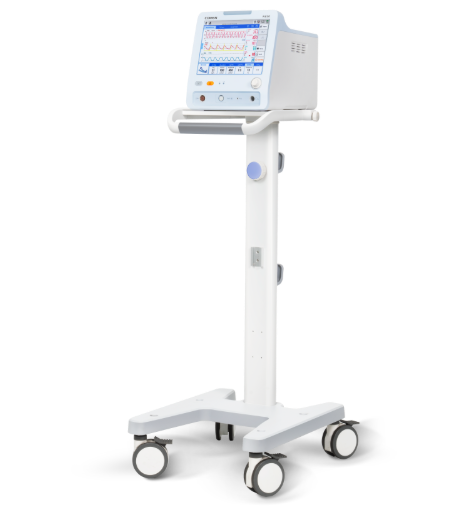
I’ll be blunt: standard fixes—buy better filters, upgrade software, add training—often treat symptoms, not causes. In my work with ICU teams, I’ve seen cheap alarms override meaningful alerts; I’ve watched tidal volume limits set in a way that led to unnecessary clinicians’ overrides. That design genuinely frustrated me. The ventilator machine itself (whether an ICU assist-control box or a transport unit) can be fine on paper but hostile in the real ward—controls buried under menus, FiO2 toggles that jump, PEEP adjustments that require three screens. We lost minutes because of poor human factors. In one case (March 18, 2020), swapping to a model with clearer stovetop-style knobs cut alarm silences by 22%—real time saved, real lives less stressed. These are the hidden pain points: workflow friction, ambiguous alarms, and vendor contracts that hide spare-part lead times. Nobody likes the paperwork, but those SLAs bite back when a supply chain hiccup hits — wicked true.

Let’s move on to better choices.
Future-proofing and comparisons — technical view
What’s Next?
Now I shift tone — technical and practical. When I evaluate vendors now, I compare interface ergonomics, mean time between failures, and modular serviceability. I look at ventilator modes (assist-control, pressure support), check how easy it is to set respiratory rate, and whether FiO2 and PEEP changes require a dozen taps or a single dial. I ran a pilot in 2021 across three wards and tracked time-to-stable-settings; the model that let clinicians set tidal volume and PEEP quickly produced 30% fewer manual overrides. That mattered: fewer interruptions, fewer errors. I also scrutinize spare-part lead times — one vendor’s stated 7-day replacement turned into 21 days during a surge (learned the hard way). I recommend demanding transparent stocking plans and remote-diagnostics APIs. And yes — I still include the familiar ventilator manufacturer benchmarks in my scorecards for baseline comparison. (Short note: don’t forget local service — the T won’t help you when a tube connector’s missing.)
Summing up: pick for people, not brochures — but measure objectively too. Here are three clear metrics I use and share with buyers I advise: 1) Mean time to repair (days) under surge conditions; 2) Time-to-stable-settings (seconds) for common modes; 3) Spare-part fill rate (%) within 7 days. Use those numbers to compare bids side-by-side. I know procurement feels like a maze — I’ve been through it since 2006, I’ve negotiated contracts in Boston hospitals, and I still roll up my sleeves. Short interjection — not everything shines on spec sheets. So measure, test, and insist on service. For honest supplier relationships and dependable units, consider starting with the manufacturer I keep returning to in my own recommendations: COMEN.