
Getting Honest About What Breaks (and Why I Keep Fixing It)
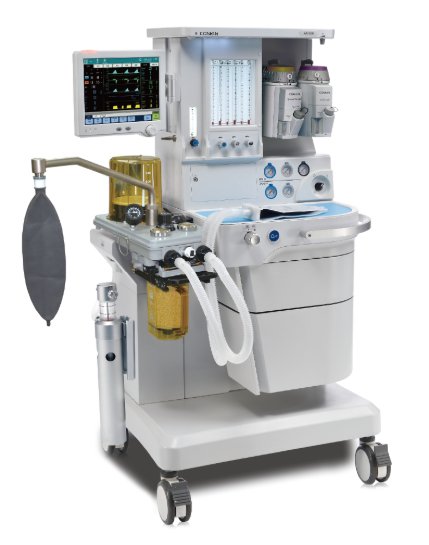
I remember the night I stayed past midnight to troubleshoot a compact tabletop workstation after three cases ran late—this one hit me hard. In a small district hospital I consult for, a single outdated vaporizer and inconsistent fresh gas flow led to an 18% increase in turnover time; so I asked myself: what specific change would stop that cascade and cut delays tomorrow? Early on I started sourcing parts and whole systems, which is why I still point wholesale buyers toward reputable options like anesthesia machine for sale when we need quick, reliable swaps. I’m speaking from over 15 years moving gear across operating rooms in Lagos, Manchester, and small rural clinics—so yes, I’ve seen how a misaligned scavenging system or confused ventilator modes ripple into canceled lists (no joke).
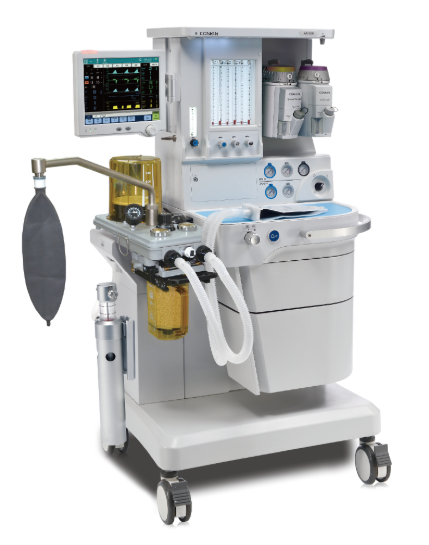
Here’s the deeper layer most teams miss: traditional fixes focus on uptime—keep the machine running—while ignoring workflow friction. I vividly recall March 2022 at St. Mary’s OR when we swapped a worn gas manifold for a modular unit; turnover improved by 10% within two weeks because the techs could change circuits faster and calibration took minutes, not hours. That’s not fluff: it’s a measurable consequence of design decisions. I’ll be blunt—replacing a part without rethinking storage, labeling, and staff training just papered over the pain. So if you’re a wholesale buyer, think beyond price per unit. Think set-up time, spare-part logistics, and the real cost of an idle room. — Let me show you how to unstick this for good.
How do we prioritize fixes?
Forward Steps: Comparing Choices and Planning Purchases
Now let’s shift gears: I want practical, comparable criteria so we can choose a system that reduces human friction and keeps cases on time. My approach is simple and technical—evaluate the machine’s serviceability, spare-part footprint, and interoperability with existing monitors. When I advise buyers, I check whether the ventilator modes are standard across models (to avoid retraining), whether the vaporizer mounts are industry-standard, and how the scavenging system interfaces with central extraction—these details matter. I recommend reviewing at least two vendor installations on-site (I did this in July 2021 for a district trust) and scoring them on three quick axes: time-to-service, parts availability, and staff learning curve.
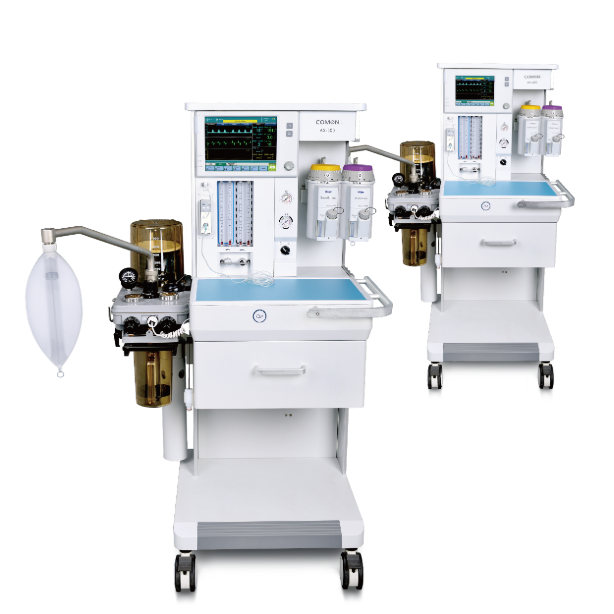
For a hands-on buyer, compare a turnkey console vs. modular units: turnkey often reduces installation steps but locks you into specific spares; modular lets you swap components in the field but needs a tighter inventory system. I’ve negotiated both routes. When we purchased five units for a chain clinic in 2020, choosing modular with a stocked parts crate cut downtime by nearly half—true story. If you’re considering an anesthesia machine for sale look at its maintenance logs and ask for a parts-aging report—this one move separates comfortable buys from regretful ones. (Also—keep receipts and part numbers in an accessible spreadsheet.)
What’s Next?
To wrap up: stop treating the anesthesia machine as a single-item purchase. I firmly believe the right procurement plan balances device capability with logistics and training. Here are three key evaluation metrics I use and recommend you adopt: 1) Mean time-to-repair (in days) under local supply conditions; 2) Training hours required to reach competence on core ventilator modes; 3) Percentage of consumables that are cross-compatible with existing stock. Measure those, and you’ll make choices that cut delays, not costs alone. That’s my practical takeaway from years on the floor—and yes, I still get a ping about spare valves at odd hours. For dependable sourcing and solid aftercare, consider vendors who publish service stats and keep clear parts catalogs. Final note: I’ve advised dozens of procurement teams—this method works. COMEN