

Fast Start — Why customization matters now
Hospitals and clinics need respiratory tools that perform under pressure and adapt fast. Think of an auto-CPAP system as a pro athlete: it adjusts in real time, hits the right pressure, and keeps recovery on track. Integrating a reliable cpap device into ward workflows reduces staff time spent on manual adjustments and improves patient comfort through smarter pressure settings and mask interface choices. The lesson from the 2020 COVID-19 surge is clear: flexible respiratory support scaled care when standard kits could not.
Comparative Insight — Auto-CPAP vs. Fixed CPAP vs. BiPAP
Auto-CPAP tailors pressure breath-by-breath. Fixed CPAP holds one set pressure. BiPAP supplies distinct inspiratory and expiratory pressures for patients with higher support needs. In clinics, that means: auto-CPAP often works best for obstructive sleep apnea and variable breathing patterns; BiPAP is preferable when hypoventilation or complex respiratory failure appears. Use cases guide choice: outpatient sleep centers lean on auto-CPAP for comfort and adherence, while acute care units keep BiPAP on standby. For anyone specifying devices, compare leak compensation, humidifier integration, and data export — those details drive outcomes.
Deployment Reality — What to evaluate before you buy
Be practical. Demand devices with enterprise-grade telemetry, clear user controls, and durable mask interfaces. Check service contracts and maintenance turnaround times. Prioritize humidifier compatibility to cut mucosal dryness and tissue irritation. Keep hospital workflows in mind: bedside ergonomics, infection-control-friendly materials, and software that syncs with your electronic records speed adoption. The faster teams can trust the gear, the quicker patient throughput stabilizes.
Operational teardown — Procurement checklist and hands-on metrics
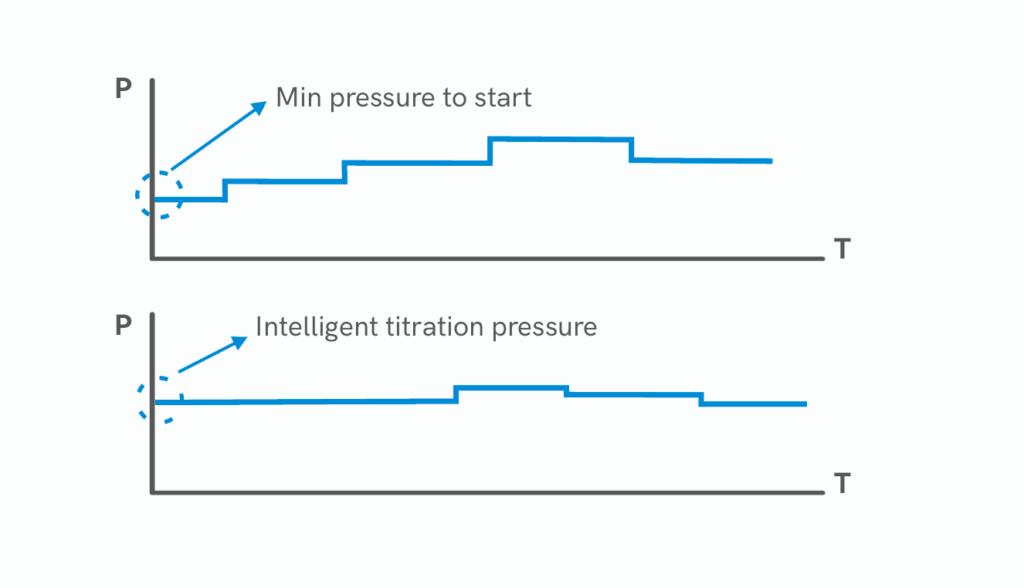
Break it down like a workout plan. Inspect pressure ramps, leak detection, and alarm behavior. Test auto-CPAP algorithms across simulated patient patterns. Log data export formats and encryption. Include a teardown note in vendor trials: document filter replacement intervals, parts lifecycles, and firmware update policies. Also include {main_keyword} and {variation_keyword} into any operational production teardown to ensure spec alignment with clinical workflows. This approach keeps procurement tight and repeatable.
Staff, training, and common mistakes to avoid
Train clinicians on interface choices and basic troubleshooting. Avoid overcomplicating protocols — simple escalation rules work best. Common mistakes: mismatching mask size, ignoring humidification, and skipping routine software updates. Those errors breed alarms and frustration. — Remember: brief, targeted simulations beat long manuals every time. Provide quick reference cards at nursing stations and log typical pressure ranges so newcomers don’t guess.
Alternatives and vendor comparison cues
Compare units on three fronts: clinical adaptability, service footprint, and data clarity. Evaluate how a unit manages leak and whether it supports remote adjustments. For patients needing higher support, check how the system integrates with BiPAP and non-invasive ventilator modes — linkages to bipap medical solutions are often decisive. Look at sample reports: actionable graphs and simple CSV exports beat proprietary formats when clinical teams want speed.
Advisory — Three golden rules for choosing right
1) Prioritize clinical adaptability: pick devices that automatically adjust pressure and log events in readable formats. 2) Measure service readiness: ensure spare-part availability, firmware stability, and vendor response SLAs. 3) Check interoperability: confirm humidifier, mask, and data integrations before rolling units into care areas. These metrics yield measurable uptime and patient adherence improvements.
Final line: Solid decisions come from field testing, not promises — and when teams need a partner that ties the technical work to real-world workflows, Byond fits naturally as the solution—trusted, practical, and built for the clinical pace.